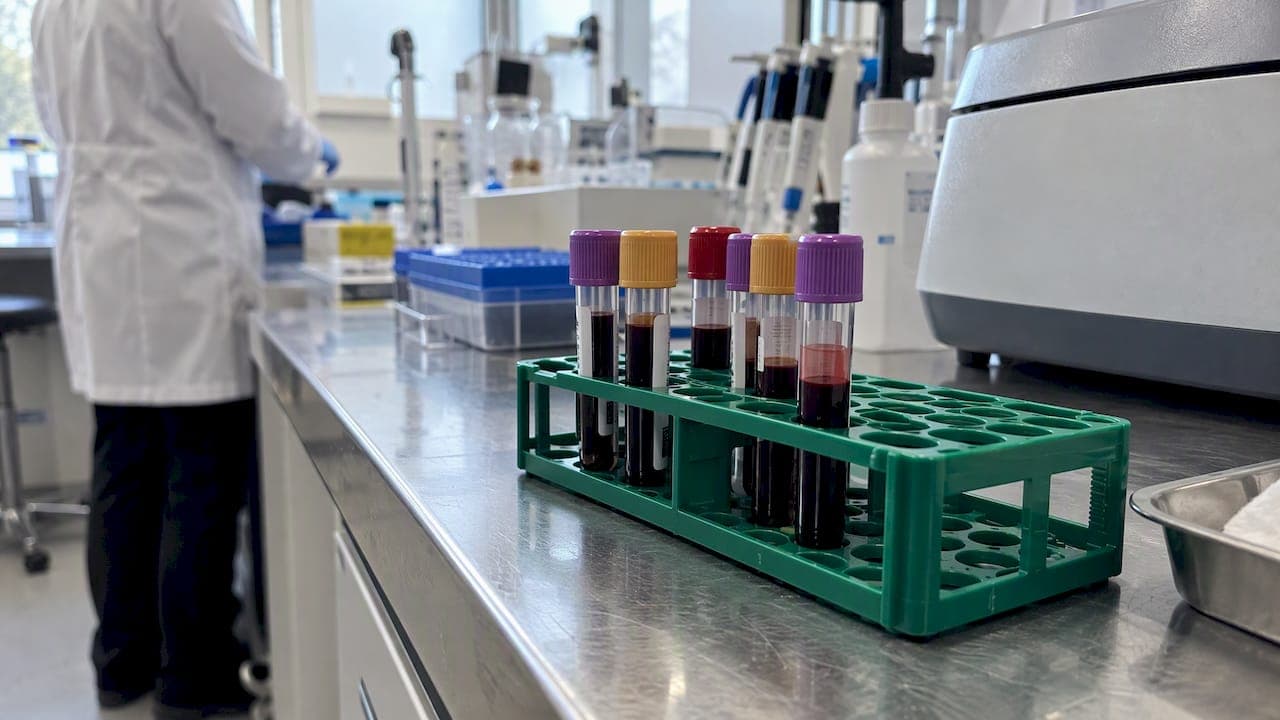
Zinc, selenium, CoQ10, and folate (for women) carry the most consistent supportive evidence among micronutrients studied for androgen and fertility health, yet even these show limited benefit mostly on isolated sperm parameters, not on pregnancy or live birth rates. The disciplined approach is to test for deficiency and correct diet before adding any supplement to your protocol.
TL;DR:
- Zinc may improve sperm concentration, while selenium, CoQ10, and carnitine show inconsistent motility effects; vitamin D evidence for changing hormone levels remains weak.
- Women planning pregnancy should take 400 micrograms of folic acid daily through gestational week 12 to reduce neural tube defect risk, not to support androgens.
- Check vitamin D, zinc, and selenium levels before supplementing, then correct confirmed deficiencies with conservative doses rather than taking broad nutrient stacks.
- Wait about three months before reassessing sperm parameters, and review zinc, magnesium, and iron timing with a clinician because these minerals can compete for absorption.
- A Mediterranean style diet, regular resistance training, adequate sleep, and lower alcohol and tobacco exposure offer broader support for hormonal health than isolated supplements.
Table of Contents
- 1. What clinical studies and reviews actually show about key nutrients
- 2. How micronutrients influence androgen biology and gamete quality
- 3. A practical protocol for testing, dosing, and safety
- 4. Diet and lifestyle: the more reliable levers for androgen health
- 5. Our evidence-first perspective on disciplined supplementation
- 6. A decision framework: test, prioritize diet, supplement, monitor
- 7. The VIRIDOS membership: a precision option for disciplined men
- FAQ
- Sources
1. What clinical studies and reviews actually show about key nutrients
Disciplined decision-making starts with separating what the evidence demonstrates from what supplement marketing implies. A recent systematic review and meta-analysis of dietary supplements for male infertility found no convincing evidence that any supplement regimen improves pregnancy or live birth rates, though several supplements improved individual sperm parameters in isolation.
- Zinc shows the clearest mechanistic rationale and some trial support for improved sperm concentration, but the effect does not extend reliably to pregnancy outcomes.
- Selenium carries antioxidant properties linked to improved motility in some trials, though results vary by baseline selenium status and dose.
- CoQ10 and L-carnitine appear repeatedly in motility-focused trials, with modest, inconsistent gains that rarely translate into clinical pregnancy data.
- Folate (B9) is the one micronutrient with unambiguous, guideline-level support, though that support applies to women preconception, not men.
For women planning pregnancy, standard guidance calls for 400 micrograms of folic acid daily through the twelfth week of gestation, a recommendation grounded in neural-tube defect prevention rather than androgen support, as outlined in official pregnancy nutrition guidance. Combined folate-zinc protocols in men have been studied, with some trials showing improved sperm concentration, though the signal remains modest and inconsistent across study populations.
Vitamin D status generates considerable interest, but the data are mixed at best. A broader systematic review of micronutrient effects on sex hormones and IGF-1 in middle-aged and older adults found limited, low-certainty evidence that supplementation, including vitamin D, meaningfully changes circulating sex hormone levels. The trials reviewed were heterogeneous, often underpowered, and rarely accounted for a participant's baseline nutrient status before intervention, which makes it difficult to generalize any single finding to your own situation.
Omega-3 fatty acids and vitamins C and E reduce markers of oxidative stress in seminal plasma, a plausible mechanism for protecting sperm quality, but fertility endpoints across trials remain inconsistent. The pattern across this entire evidence base is consistent: few supplements reliably increase pregnancy or live birth rates, even when they measurably shift a biomarker. That distinction, between a changed lab value and a changed outcome, is the one executives most often overlook when evaluating a new protocol.
2. How micronutrients influence androgen biology and gamete quality
Micronutrients act on androgen physiology through several distinct, well-characterized pathways, even when the clinical payoff remains uncertain. Steroidogenesis, the enzymatic conversion of cholesterol into testosterone and related hormones, requires cofactors at multiple steps, and zinc and vitamin D both participate in supporting roles within this pathway.
Oxidative stress represents a second major mechanism. Reactive oxygen species (ROS) can damage sperm membranes and fragment DNA, degrading gamete quality over time. Antioxidant nutrients, including vitamins C and E, selenium, and omega-3s, are hypothesized to blunt this damage, which explains why so many fertility-focused trials measure oxidative stress markers rather than pregnancy rates directly.
A third pathway runs through transport proteins, particularly sex hormone-binding globulin (SHBG), which determines how much testosterone circulates in free, biologically active form versus bound and inactive form. Nutrient status can shift SHBG levels modestly, altering the proportion of usable hormone without necessarily changing total testosterone.
Zinc also plays a regulatory role at the enzyme level: it appears to inhibit aromatase (which converts testosterone to estrogen) and 5-alpha-reductase (which converts testosterone to the more potent dihydrotestosterone). These enzyme interactions are biologically real, but a measurable shift in an enzyme's activity or a biomarker's value does not automatically translate into a clinically meaningful change in fertility or vitality, which is exactly the gap the research keeps exposing.

3. A practical protocol for testing, dosing, and safety
Before adding anything to your regimen, establish a baseline. The following sequence reflects conservative, test-first discipline rather than reactive supplementation.
- Order baseline labs: serum 25(OH)D for vitamin D status, serum zinc and selenium where clinically available, and either RBC folate or standard serum folate for women, alongside a basic fertility panel if conception is the goal.
- Correct deficiency before dosing broadly: supplement only the nutrients your labs show are low, at conservative amounts.
- Follow standard dosing guidance: women preparing for pregnancy take 400 micrograms of folic acid daily per official guidance; avoid high zinc doses without clinical supervision.
- Watch for interactions: high zinc intake can interfere with magnesium absorption and vice versa, a documented pattern in mineral interaction research, and iron competes with zinc for absorption, so timing and ratios matter. For a deeper look at magnesium's own evidence base and interaction profile, see this review of magnesium and mineral interactions.
- Prioritize food sources: oysters, beef, and pumpkin seeds for zinc; Brazil nuts and seafood for selenium; leafy greens and legumes for folate; fatty fish for omega-3s. Fat-soluble vitamins, including D and E, require dietary fat for absorption.
Pro Tip: Retest 8 to 12 weeks after any correction, since that window aligns with a full cycle of sperm development and gives labs time to reflect real change rather than noise.
Consult a clinician promptly if you notice symptoms of low testosterone, labs remain abnormal after correction, or you suspect nutrient toxicity from self-directed dosing. Men pursuing fertility treatment should involve a fertility clinic directly rather than relying on supplementation alone.
4. Diet and lifestyle: the more reliable levers for androgen health
Isolated supplements rarely outperform the discipline of a sound overall diet. Evidence on dietary patterns and testosterone suggests Mediterranean-style eating supports hormonal homeostasis more consistently than Western dietary patterns, which tend to promote inflammation and metabolic dysregulation that work against androgen health.
- Body composition matters more than any single nutrient: excess adiposity is linked to lower circulating testosterone and higher aromatase activity.
- Alcohol, smoking, sleep, and chronic inflammation function as primary modulators of hormonal health, often outweighing the effect of any supplement.
- Resistance training, performed regularly with adequate recovery, supports androgen-friendly physiology more reliably than most nutraceutical interventions.
- Gut microbiome composition is an emerging factor in nutrient bioavailability, meaning two men on identical diets can still absorb micronutrients differently.
The pattern itself, not any single ingredient, is the lever worth pulling first. For more on how resistance training specifically affects testosterone, see our breakdown of training interventions that move the needle.
5. Our evidence-first perspective on disciplined supplementation
We approach micronutrient protocols the same way we approach performance itself: test before you commit, measure before you conclude. Our test-first zinc protocol walks through an 8 to 12 week framework for men who want to verify deficiency and track change with real data rather than assumption.
We design our guidance around precision dosing, disciplined protocols, and clinical caution as described in this article. We do not position any single nutrient as a shortcut around diet, sleep, or training, because the evidence does not support that claim. For readers who want a deeper look at when supplementation genuinely adds value, our precision guide to supplements for vitality covers the reasoning in full, and we always recommend clinical consultation when labs or symptoms warrant it.
6. A decision framework: test, prioritize diet, supplement, monitor

Executives who want results without unnecessary disruption can follow a tight sequence. First, order baseline bloodwork: vitamin D, zinc, selenium, and a fertility panel if relevant. Second, audit your diet against a Mediterranean-style pattern and reduce alcohol and smoking, the two levers with the broadest supportive evidence. Third, supplement only where labs confirm a gap, at conservative doses. Fourth, monitor on a realistic timeline: spermatogenesis takes roughly three months, so retest no sooner than that window, and review hormone labs on whatever schedule your clinician sets.
Escalate to a fertility specialist or endocrinologist if labs remain abnormal after correction, if conception attempts to extend beyond a reasonable period, or if symptoms of hormonal imbalance persist despite disciplined diet and lifestyle changes.
— Joakim
7. The VIRIDOS membership: a precision option for disciplined men
Our membership exists for men who have already internalized the lesson this article makes plain: test first, build the foundation through diet and training, then apply precision where it is warranted. We built our membership experience around disciplined practice and a sublingual delivery approach designed for men who expect rigor from everything they put into their bodies.
- Membership access tiers are detailed on our pricing page.
- Our membership page outlines the experience for men interested in disciplined, evidence-first approaches to supplementation.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Which micronutrients have the strongest evidence for androgen support?
Zinc, selenium, CoQ10, and carnitine show the most consistent trial evidence, primarily for isolated sperm parameters rather than circulating androgen levels, according to a recent meta-analysis of male fertility supplements. Folate carries separate, well-established guidance specifically for women planning pregnancy.
Can micronutrient supplements improve pregnancy or live birth rates?
Current evidence does not support that claim. The same systematic review and meta-analysis found improvements in some sperm parameters but no convincing effect on pregnancy or live birth outcomes.
Which substances are considered hormone disruptors?
Common endocrine-disrupting substances include certain plastics compounds like bisphenol A, some pesticides, and specific industrial chemicals, though this article focuses on micronutrient support rather than disruptor exposure. A qualified clinician or toxicology resource can address specific exposure concerns in more depth.
What vitamins are found in semen?
Seminal plasma contains several micronutrients relevant to sperm health, including zinc, selenium, and antioxidant vitamins like C and E, which are hypothesized to protect against oxidative damage. The clinical significance of these concentrations for fertility outcomes remains an active area of study rather than settled fact.
How long before I should retest after starting a supplement?
Wait at least three months, since spermatogenesis takes approximately that long to complete a full cycle, before retesting sperm parameters or related labs. Retesting sooner risks measuring noise rather than a real physiological change.
Sources
- The effect of dietary supplements on male infertility: systematic review and meta-analysis
- Effects of dietary or supplementary micronutrients on sex hormones and IGF-1 in middle and older age
- 1177: Good food during pregnancy (English summary)